

Table of Contents
- Common Nutritional Deficiencies in Children: What Parents Should Know
- Physical Signs and Symptoms of Nutritional Deficiencies in Children
- Behavioural and Cognitive Signs: How Deficiencies Affect Focus and Mood
- Picky Eating or Clinical Deficiency? Knowing the Difference
- Best Vitamins for Picky Eaters: Filling the Gaps Without the Battle
- When to See a GP and What Blood Tests Can Tell You
- Frequently Asked Questions
Last Updated: September 14, 2026
Common Nutritional Deficiencies in Children: What Parents Should Know
Spotting the signs of nutritional deficiencies in children early is one of the most useful skills you can develop as a parent, because the earliest clues are usually behavioural and easy to dismiss as tiredness or a phase. Below, we'll walk through what to look for, how to tell a genuine deficiency from ordinary fussy eating, and when it's worth asking your GP for a blood test.
Iron Deficiency Anaemia
Iron deficiency anaemia is the most common nutritional shortfall in young children, and it develops slowly. Haemoglobin carries oxygen around the body, so when iron runs low, children tire quickly, look pale, and lose concentration. The NHS advises that children aged one to three need around 6.9mg of iron a day, which is hard to hit if a child eats mostly white pasta and toast (the NHS). A common mistake is assuming a "good eater" is covered; a child can eat plenty of calories and still miss iron entirely.
Vitamin D Deficiency
Vitamin D deficiency is widespread in children because sunlight exposure is limited for much of the year. The NHS recommends that children aged one to four take a daily supplement of 10 micrograms of vitamin D, and babies from birth to one year need 8.5 to 10 micrograms (the NHS). Low vitamin D shows up as muscle weakness, bone pain, and delayed walking, and it also affects how well the body absorbs calcium. It is the one deficiency where a supplement is standard advice rather than a last resort.
Calcium and Other Key Nutrients
Calcium supports bone growth, and low intake over time weakens bones rather than causing obvious day-to-day symptoms. Vitamin B12, zinc, and omega-3 fats also matter for energy, wound healing, and immune function. Children following restricted diets, whether by choice or because of sensory issues, are most at risk of missing several of these at once. A simple rule: the more limited the menu, the more likely a gap is forming.
Physical Signs and Symptoms of Nutritional Deficiencies in Children
The physical signs of nutritional deficiencies in children are often subtle at first and easy to miss in normal family life. What makes them tricky is that the same outward sign can point to different nutrients depending on your child's age, diet and how long the gap has been forming. The table below maps what you might notice at home to the nutrient most often behind it, and the mechanism that explains why.
| What you might see | Likely nutrient gap | Why it happens | What to do next |
|---|---|---|---|
| Pale skin, pale inner eyelids | Iron | Haemoglobin needs iron to carry oxygen; low stores mean less colour in the blood | Ask your GP about a blood test |
| Tiredness, irritability | Iron, B12 | Red blood cells can't deliver oxygen efficiently, so muscles and brain tire faster | Review iron-rich foods and consider a blood test |
| Muscle weakness, bone pain, delayed walking | Vitamin D, calcium | Vitamin D governs how calcium is absorbed; without it, bones soften | Consider a daily vitamin D supplement |
| Slow wound healing, frequent mouth sores | Zinc, vitamin C | Both are needed for collagen formation and immune cell repair | Check fruit, veg and protein intake |
| Frequent infections, longer recovery | Zinc, vitamin D | Immune cells depend on these nutrients to mount a fast response | Discuss with your GP |
| Cracked lips, sore tongue | B vitamins (B2, B3, B12) | These vitamins maintain the mucous membranes lining the mouth | Review diet variety; ask about testing |
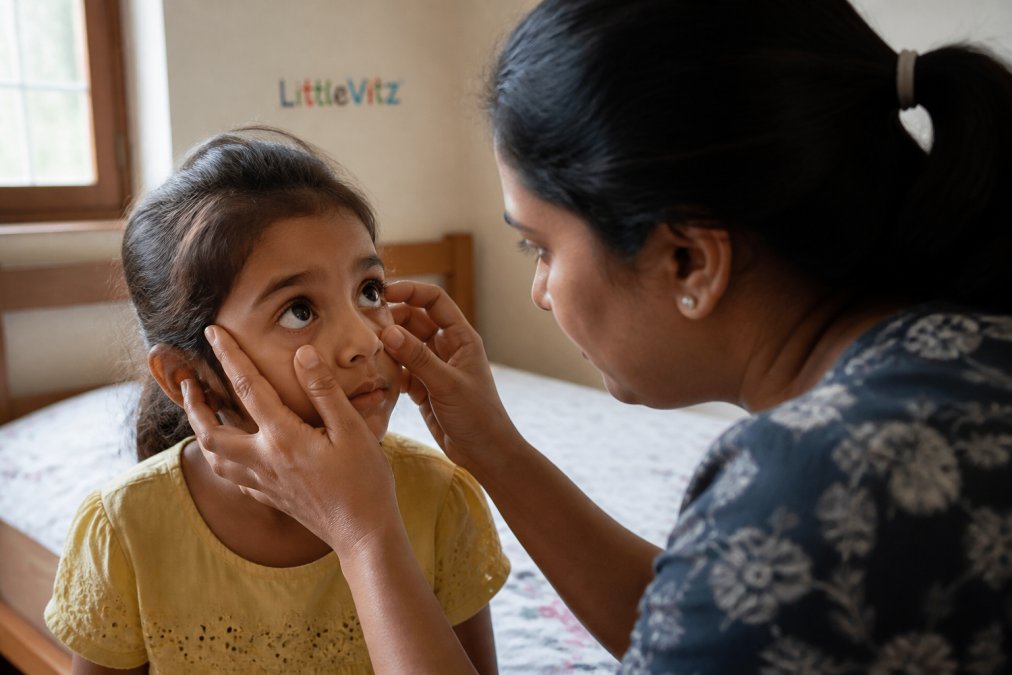
What You Might See at Home
Pallor, or unusual paleness, is the classic clue, and it is easiest to spot by gently pulling down the lower eyelid to check the colour inside, a healthy inner eyelid should be a rich pink-red, not pale pink or white. Fatigue and irritability often appear first, before anything visible changes, because the brain is one of the first organs to feel a drop in oxygen delivery. Poor appetite can be both a cause and a symptom, which is why the cycle is so hard to break: a child low in iron or zinc may eat less, which deepens the gap. In practice, this means a child who seems "just tired" for weeks deserves a second look rather than a nap.
A useful habit is to check the same things at the same time each week, inner eyelids, energy at breakfast, nail colour, and how quickly small cuts heal. Patterns over weeks tell you far more than a single snapshot.
Age-Specific Signs: Toddlers vs. School-Age Children
This is where most guides lump all children together, and it is the single biggest reason parents miss the early clues. The same deficiency looks completely different depending on your child's stage of development.
Toddlers (1-3 years) are in a window of rapid brain and bone growth, so deficiencies tend to show up as delayed milestones, later walking, fewer words than expected, slow growth on the growth chart, and frequent infections. Because toddlers are famously fussy, parents often attribute these signs to personality rather than nutrition.
School-age children (4-11 years) are more likely to show it through poor concentration, falling behind at school, irritability at homework time, and muscle weakness during play. Teachers may notice before parents do.
Teenagers (12+), especially those eating restricted diets, following a plant-based diet without planning, or going through growth spurts, often present with persistent fatigue, difficulty concentrating, and, in girls, heavier periods that worsen iron loss. The same iron deficiency that causes pallor in a toddler may cause falling grades in a teenager.
Signs That Need Prompt Attention
Most nutritional gaps develop slowly, but a few signs warrant a same-week GP appointment rather than a wait-and-see approach: unusual paleness combined with breathlessness or a racing heartbeat, refusal to weight-bear or unexplained bone pain, a growth curve that has flattened or dropped, and any regression in skills your child had already mastered. These do not automatically mean a deficiency, but they are the situations where a blood test is genuinely useful rather than reassuring.
Behavioural and Cognitive Signs: How Deficiencies Affect Focus and Mood
Behavioural changes are frequently the first sign that something is missing, and they are the ones parents most often blame on temperament. Iron deficiency is strongly linked to poor concentration and irritability, while low vitamin D and B12 affect mood and energy. If you want to know how to boost child focus naturally, the honest answer is that focus starts with nutrition, not willpower. A child who cannot sit still at the table may simply be running low on the nutrients that support attention. Establishing a robust foundation of essential vitamins and minerals does more than stabilize daily behavior, as these same nutritional building blocks are vital to boost child immunity throughout the changing seasons.
Picky Eating or Clinical Deficiency? Knowing the Difference
Picky eating is a normal developmental stage; a clinical deficiency is a measurable shortfall that affects how the body works. The distinction matters because one needs patience and the other may need medical input. A common approach is to ask three questions:
- Has your child eaten fewer than 20 different foods for more than a month?
- Have they dropped a food group entirely, such as all fruit or all meat?
- Are there physical signs, like pallor or slow growth, alongside the fussiness?
If you answered yes to two or more, it is worth raising with your GP rather than waiting for it to resolve. Sensory issues and ARFID sit at the more serious end of this spectrum and often need professional support.
Best Vitamins for Picky Eaters: Filling the Gaps Without the Battle
The best vitamins for picky eaters are the ones your child will actually take every day, because consistency matters more than a long ingredient list. Supplements and fortified foods can bridge a gap, but they work best alongside, not instead of, real food. This is where LittleVitz comes in: our chocolate-flavoured Kids Super Greens powder contains over 20 superfoods plus essential vitamins and minerals, with no added sugar, so it mixes into milk or a smoothie without a fight. If you want to test it first, the Kids Super Greens Trial & Travel Pouch gives you five servings to try. For families ready to commit, the full Kids Super Greens - 25 Servings offers a larger supply.


When to See a GP and What Blood Tests Can Tell You
See your GP if your child shows persistent pallor, fatigue, poor growth, or developmental delays, or if a restricted diet has lasted more than a few weeks. A GP can arrange blood work to check serum levels of iron, ferritin, vitamin D, and other markers, alongside a physical examination and growth charts plotted against UK growth standards.
Most parents leave the appointment with a printout of numbers and no clear sense of what they mean. This section is the plain-English guide that most articles skip.
What the Common Markers Actually Mean
Ferritin measures your child's iron stores, not the iron currently circulating. This is the single most useful early marker, because ferritin can be low while haemoglobin still looks normal, a state called iron depletion, where your child has no reserve left but is not yet anaemic. Many parents are told "the blood count is fine" when ferritin was never checked. If your child is tired and pale but the full blood count looks normal, ask specifically whether ferritin was measured.
Haemoglobin measures the oxygen-carrying capacity of the blood. Low haemoglobin confirms anaemia, but it is a late sign, by the time it drops, iron stores have usually been depleted for some time. This is why ferritin matters more for catching a problem early.
Vitamin D is measured as serum 25-hydroxyvitamin D. Results are usually described in nanomoles per litre (nmol/L). The NHS advises that a level below 25 nmol/L indicates deficiency, while 25-50 nmol/L is often described as insufficient (the NHS). Levels vary seasonally, so a test taken in late winter may look very different from one taken in summer.
Vitamin B12 and folate are usually checked together, because a deficiency in either can cause similar symptoms, tiredness, irritability, and in more serious cases, tingling in the hands and feet. B12 is especially worth checking in children following a vegan diet without fortified foods or supplements.
Zinc and vitamin C are less commonly tested on the NHS, because blood levels fluctuate and do not always reflect true body stores. A GP may rely more on dietary history and symptoms for these.
Questions Worth Asking at the Appointment
- Was ferritin measured, or only the full blood count?
- What is the actual number, and where does it sit within the normal range for my child's age?
- Should we retest in a few months to see whether the level is improving?
- Does this result change what we should be doing at home?
What Happens Next
If a deficiency is confirmed, the GP may prescribe a specific supplement at a therapeutic dose rather than a general multivitamin, for example, a prescribed iron or vitamin D preparation. Do not start a high-dose supplement on your own, because some nutrients, particularly iron and vitamin A, can be harmful in excess for young children. Your GP may also refer you to a paediatric dietitian if the cause is a restricted diet, sensory feeding difficulty, or a suspected absorption problem.
The NHS guidance on vitamins for children is a good starting point before your appointment, and it explains the standard supplement recommendations for each age group.
Frequently Asked Questions
How do I know if my child has a nutrient deficiency?
Watch for persistent tiredness, pale skin, irritability, poor concentration, frequent infections, or slowed growth. These can point to low iron, vitamin D, or other nutrients. A GP can arrange a blood test to confirm. Keeping a simple food diary for a week before your appointment helps the GP see your child's typical dietary intake and spot likely gaps quickly.
Can nutritional deficiencies affect a child's focus and behaviour?
Yes. Low iron and vitamin D are linked to poor concentration, irritability, and lower energy in children. If you are wondering how to boost child focus naturally, addressing underlying nutrient gaps is a sensible first step alongside good sleep and outdoor play. A GP can check serum levels if you are concerned about your child's attention or mood.
What are the most common vitamin deficiencies in children?
Iron deficiency anaemia and vitamin D deficiency are the most frequently seen in young children. Calcium intake can also fall short, especially when dairy is limited. Picky eaters, children with restricted diets, and those with malabsorption conditions face higher risk. Fortified foods and a child-friendly supplement can help bridge gaps when dietary intake alone is not enough.
When should I consult a GP about my child's diet?
Book a GP appointment if your child shows physical signs such as pallor, muscle weakness, bone pain, or poor wound healing, or if they are falling behind on growth charts. Also seek advice if mealtimes are consistently stressful, if your child avoids entire food groups, or if you suspect failure to thrive. Early pediatric assessment can rule out underlying conditions.
How does a lack of iron or vitamin D impact child development?
Iron is essential for cognitive development and oxygen transport; low levels can cause fatigue, poor concentration, and delayed developmental milestones. Vitamin D supports bone growth and immune function, and deficiency can lead to bone pain and muscle weakness. Both are easily checked with blood work and addressed through dietary changes, fortified foods, or supplements.
Are supplements safe for picky eaters, and how do I choose one?
Children's supplements are generally safe when used as directed, but choose one formulated for your child's age and free from added sugar or artificial sweeteners. The best vitamins for picky eaters are easy to mix into food or drink, taste pleasant, and contain a broad range of vitamins and minerals rather than a single nutrient, unless your GP recommends otherwise.
Every parent worries about whether their child is getting enough, and the good news is that most gaps are fixable once you know where to look. If mealtimes have become a battleground, LittleVitz makes it easier to close the gap: our chocolate Kids Super Greens blend over 20 superfoods with essential vitamins, no added sugar, and a taste children actually ask for. Start with a trial pouch, or go straight to the 25-serving tub and turn the daily veggie fight into a treat they look forward to.